Myofascial Pain Syndrome vs Fibromyalgia: Why Most Doctors Get It Wrong and What the Right Treatment Is
A patient often comes to my clinic with normal reports and one simple question: "Doctor, if my MRI and blood tests are normal, why is my neck and upper back hurting every day?" Some have been told it is myofascial pain. Others have been told it is fibromyalgia, and some have been told it is only stress.
The two conditions can feel similar. Both may cause aching muscles, stiffness, tiredness and poor sleep, and both are easily missed because routine scans may look normal. But they are not the same condition, and treating one as if it were the other can delay relief.
The key difference is the main source of pain. Myofascial pain begins in specific overloaded muscles and trigger points. Fibromyalgia is a wider problem in which the nervous system becomes more sensitive to pain signals. Some patients have both. This guide explains myofascial pain syndrome treatment India, how I separate MPS from fibromyalgia, and what treatment helps.

Noida Pain Management Clinic, Sector 117
What Is Myofascial Pain Syndrome?
Myofascial pain syndrome, often shortened to MPS, is a painful muscle condition caused by sensitive spots in muscles and the surrounding connective tissue, called fascia. Pain is usually limited to one region, such as the neck, shoulder, upper back, jaw, buttock or one side of the body. It develops when a muscle is repeatedly overloaded, held in one position too long, injured, or forced to compensate for a weak or painful joint nearby.
When I examine a patient, I press the muscles systematically, check movement and posture, and look for tissue that reproduces the familiar pain. This examination is central because trigger points are clinical findings and do not appear clearly on routine scans. A normal MRI therefore does not rule out MPS.
MPS may settle after a strain, but it becomes chronic when the overload continues: raised shoulders at a desk, repeated turning towards a board, or lifting and carrying without recovery. Unless the pattern changes, the muscle remains irritable.
What Are Trigger Points: The Core of MPS
A trigger point is a small, highly sensitive area in a tight band of muscle. Patients often call it a knot. Pressing an active trigger point reproduces the patient's usual pain and may send it to another predictable area. This is called referred pain.
An upper trapezius trigger point can refer pain to the temple and cause headache. A shoulder blade trigger point can send pain down the arm. A deep buttock trigger point can imitate sciatica by referring pain into the back of the thigh. MPS is therefore sometimes mistaken for a slipped disc, nerve compression or joint disease.
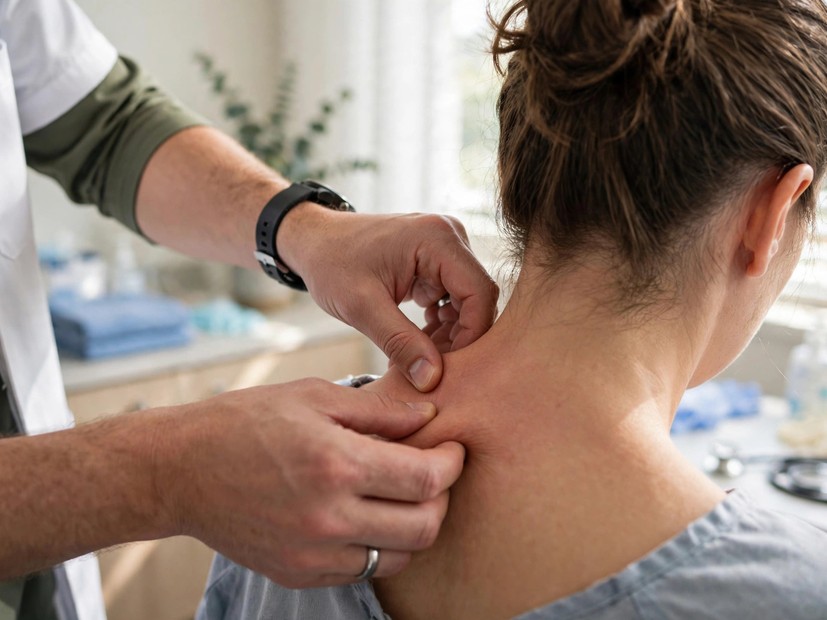
Pressure may produce a quick contraction in the tight band, called a local twitch response. An active point causes pain during daily activity. A latent point may hurt only when pressed but can still restrict movement.
Overload, reduced local blood flow and protective tightening maintain trigger points. Poor sleep, stress, prolonged posture, sudden exercise and untreated joint or spine pain keep the cycle active. Treating only the spot usually gives temporary relief.
Who Gets MPS Most Often (IT Workers, Teachers, Bank Staff)
I see MPS frequently in IT professionals who use a laptop for long hours and sit with the head pushed forward. Teachers develop trigger points from writing, standing, speaking and carrying books. Bank staff sit through long public dealing hours, often on poorly fitting chairs and with few breaks.
It is also common in homemakers, dentists, drivers, tailors, factory workers and long distance two wheeler commuters. The common thread is repeated load in a limited set of muscles, sustained posture, weak supporting muscles, disturbed sleep and too little recovery.
MPS may also follow whiplash, a sports strain, an operation, bed rest or a painful joint. Sometimes it is the main diagnosis; sometimes it is secondary to cervical spondylosis, a disc problem or joint disease.
MPS pain starts in specific overloaded muscles and trigger points, and stays local or regional.
Fibromyalgia pain is widespread, because the nervous system becomes more sensitive to pain signals.
Some patients have both, which is why the examination, not a single test, decides the treatment.
MPS vs Fibromyalgia: Why They Are Constantly Confused
Fibromyalgia is a long term condition marked by widespread pain, fatigue, unrefreshing sleep and increased sensitivity to touch, sound or temperature. Headaches, bowel symptoms and poor concentration are common. It does not cause joint destruction or muscle damage. The main problem is altered pain processing in the brain and spinal cord, called central sensitisation.
Both conditions involve tender muscles and can worsen with stress and poor sleep, and they can overlap. The goal is to decide which mechanism is dominant and what treatment should come first.
| Feature | Myofascial Pain Syndrome | Fibromyalgia |
|---|---|---|
| Pain pattern | Local or regional, often one side, with referred pain from trigger points | Widespread, often both sides and above and below the waist |
| Tender spots | Trigger points in tight bands; pressure reproduces and may refer familiar pain | Sensitive areas hurt locally but usually show no clear referral pattern |
| Main problem | Overloaded muscle and fascia from posture, injury or a nearby joint or spine problem | Altered central pain processing, fatigue and unrefreshing sleep |
| Diagnosis method | History and examination for taut bands, referral and restricted movement | Symptom pattern and duration, with tests to rule out other diseases |
| First line treatment | Deactivate points, correct overload, stretch, strengthen and use physical therapy | Graded exercise, sleep and stress care, medicines and multidisciplinary care |
| Response to trigger point injection | Often useful when an active point is a major pain driver | Not the main treatment for widespread pain, though it may help a separate local MPS component |
Key Differences in Symptoms
In MPS, the patient can usually identify a region and pattern. The neck may feel tight on one side, turning may be limited, and pressing between the shoulder blades may recreate headache or arm ache. Pain is often deep, burning or heavy and changes with posture, heat or stretching.
In fibromyalgia, pain is harder to localise and may move between body regions. Light touch, poor sleep or stress can make the whole body ache. Fatigue and non refreshing sleep are more prominent, while progressive weakness and joint swelling are not direct features.
Fibromyalgia usually persists for at least three months. MPS may be acute or persist if the cause continues, so duration alone cannot make the diagnosis.
Widespread pain with swollen joints, morning stiffness over an hour, fever, rash, major weight loss or true weakness needs evaluation for inflammatory or systemic disease.
Chest pain, exertional jaw pain, breathlessness or sweating must be assessed urgently, never assumed to be a trigger point.
Why Wrong Diagnosis Leads to Wrong Treatment
If fibromyalgia is mistaken for MPS, repeated local injections may be given while sleep disturbance, deconditioning, stress sensitivity and widespread pain remain untouched.
If MPS is mistaken for fibromyalgia, long term medicines may be given while a treatable trigger point in the neck, shoulder blade or buttock continues to generate daily symptoms.
Wrong labels also create fear. Fibromyalgia does not mean muscles are permanently damaged, and one injection cannot erase years of overload.
Not Sure Whether It Is MPS or Fibromyalgia?
Get the diagnosis right first. A careful muscle examination at Noida Pain Management Clinic can separate a treatable trigger point from widespread pain sensitivity.
Symptoms of MPS You Should Know
MPS pain is often a deep ache, tightness, burning, heaviness or a painful knot. It may worsen through the workday and ease partly with rest, heat or gentle movement. Flexibility may reduce, and pain may travel without following the exact path of a nerve.
MPS does not usually cause true weakness, loss of reflexes or clear skin numbness. Those findings need assessment for a spine, joint or nerve cause.
Burning, Heaviness in Neck and Upper Back
The neck and upper back are the sites I see most often. Their muscles become overloaded when the head is forward, the shoulders stay raised, or a phone is held between the ear and shoulder. Patients may wake stiff, ache by afternoon and feel burning between the shoulder blades after computer work.
Some develop headaches at the base of the skull or behind the eye, or pain around the jaw, ear or shoulder. I ask where the pain starts and travels, then check whether pressing a muscle reproduces that map.
Pain That Worsens Despite Physiotherapy
Patients sometimes say, "I have done physiotherapy, but the pain keeps coming back." That does not mean physiotherapy failed. General exercises may not help if the active point was missed, strengthening begins too early, or workstation load remains unchanged. Aggressive stretching or deep pressure during a flare can also increase pain.
An untreated driver may be responsible: a cervical disc problem can irritate neck muscles, while a painful shoulder makes the upper back overwork. Poor sleep, vitamin deficiency, thyroid disease, anaemia or diabetes may also need checking. Good physiotherapy should be specific, not generic.
Disturbed Sleep and Fatigue
Pain can disturb sleep even in pure MPS. A patient may be unable to lie on the painful side, may wake when turning, or may start the morning stiff. Poor sleep lowers pain tolerance the next day, especially during deadline pressure, family stress or travel.
Fatigue in MPS often follows pain, poor sleep and guarding. In fibromyalgia, it is broader and may occur even when local pain is not severe. Extreme exhaustion, snoring, thyroid disease, anaemia or depression should be assessed separately.
Correct Treatment for Myofascial Pain
Correct treatment has three parts: confirm the diagnosis, deactivate the trigger points and remove the overload that created them. Doing only the second part often gives temporary relief. Complete rest can also make muscles weaker and less tolerant. The plan should be active, measured and reviewed.
Initial care may include short term medicines, heat, stretching, manual therapy, posture correction and gradual strengthening, plus attention to sleep and work breaks. When an active point remains painful or pain is severely limiting, a trigger point injection can help. It is not a shortcut around rehabilitation.
Trigger Point Injection: What It Does and What to Expect
A trigger point injection is a small injection into the painful knot after it has been located by examination. It may use a local anaesthetic, sometimes with another medicine selected by the treating doctor. The aim is to interrupt the pain and spasm cycle, reduce sensitivity and make stretching and strengthening easier.
For deep muscles or points close to important structures, I may use ultrasound guidance to identify the muscle and nearby vessels and nerves. Not every superficial point needs guidance, but the site should never be approached casually.
Trigger point injections need specialized injection techniques. A pain management specialist is the one we should be looking to consult for long term relief.
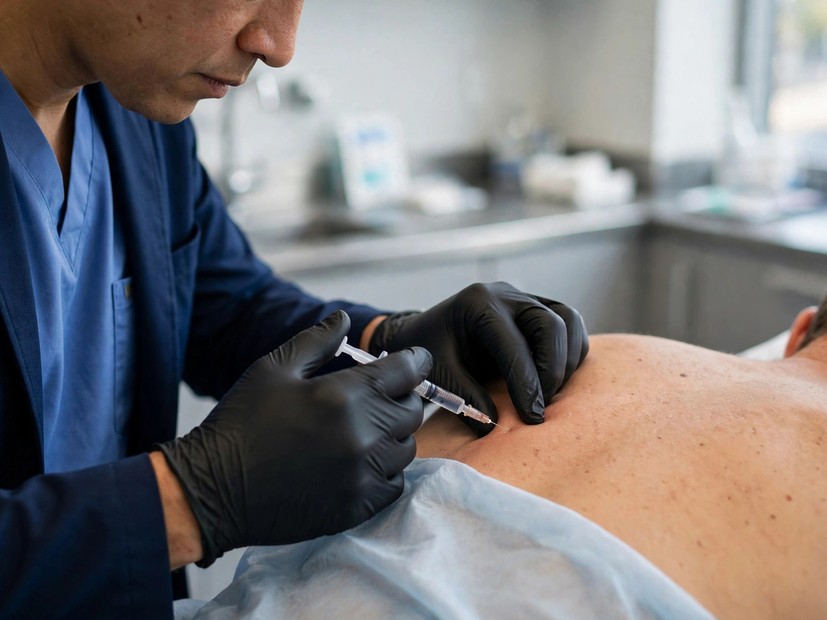
You may feel a brief prick and pressure. When the needle enters an active point, the muscle may give a quick twitch. This local twitch response is common and often confirms the spot. Afterwards, soreness, heaviness or a bruise can occur for one to two days. Gentle heat and prescribed stretching are often advised once soreness settles.
Risks include bleeding, infection, temporary pain increase, nearby structure injury and, around the chest wall or neck, rare deeper complications. Tell your doctor about blood thinners, allergies, pregnancy, local infection and previous reactions to local anaesthetic.
The injection is not a miracle cure. If the same posture, weak muscles or untreated joint problem remains, the point can become active again. Its best use is as a window of relief in which rehabilitation can progress.
Nerve Medications and NSAIDs
Medicines depend on the pain pattern, other medical conditions and previous response. NSAIDs such as ibuprofen or diclofenac may help short term pain, but they are not a long term solution for most MPS patients. They can irritate the stomach and affect the kidneys, blood pressure and heart risk, so they should not be taken daily for months without supervision.
A short course of a muscle relaxant may be considered for severe spasm, although drowsiness can limit use. When pain has a nerve like quality, disturbs sleep or becomes persistent, a doctor may consider amitriptyline, duloxetine, pregabalin or gabapentin. These can cause sleepiness, dizziness, dry mouth and other effects and must be started, adjusted and stopped under supervision. They are more central to fibromyalgia care than to a simple local trigger point.
For fibromyalgia, medicines are only one part of long term care. Graded exercise, sleep and stress care, mood treatment and activity pacing are equally important. Rheumatology input may be needed to exclude inflammatory disease. Never increase pain medicines on your own.
Stretching Protocol
Stretching should be gentle, slow and pain guided. Never force a stretch, bounce or hold a painful end range. Breathe normally, keep the shoulders low and stop if pain radiates, tingles or worsens sharply.

A safe starting routine for many desk workers includes:
- Chin tucks: sit upright, gently draw the chin back and hold for five seconds, repeat ten times.
- Neck side bend: tilt the ear towards the shoulder until a gentle stretch is felt, hold for fifteen seconds on each side.
- Shoulder blade squeeze: gently draw the shoulder blades together and down, hold for five seconds, repeat ten times.
- Chest opening: place the forearms on a door frame, step forward gently until the chest stretches, hold for fifteen seconds.
- Upper trapezius stretch: sit on one hand, tilt the head away from that side, hold for fifteen seconds, repeat on both sides.
- Gentle upper back rotation: sit tall and rotate slowly to each side within a comfortable range, repeat five times each way.
Afterwards, posture and strengthening matter more than stretching alone. Weak deep neck flexors, mid back muscles and shoulder blade stabilisers often need gradual strengthening once pain settles.
Workstation changes help: keep the screen at eye level, elbows supported, feet flat and the keyboard close. Take short movement breaks every thirty to forty five minutes. If pain worsens during work, the setup, not only the muscle, needs review.
Myofascial Pain Treatment at Noida Pain Management Clinic
At Noida Pain Management Clinic, my approach starts with careful history and examination. I check the painful muscles, referral pattern, joint and spine, nerve signs, posture, work habits, sleep and previous treatment. That determines whether MPS is the main problem, whether fibromyalgia is more likely, or whether both are present.
Treatment is planned stepwise. Many patients improve with specific physiotherapy, stretching, posture correction, ergonomic advice and short term medicines. When an active point remains a major driver, a trigger point injection may be offered, with ultrasound guidance where needed. Other causes are not ignored: cervical spondylosis, disc problems, shoulder disease, inflammatory disease and nerve problems are assessed and referred appropriately.
Patients are told what to expect, what to avoid and when to return. Aggressive daily deep massage, repeated injections without rehabilitation, long term daily NSAIDs and self adjusting pain medicines are avoided. Improvement is judged by function, not only pain score: sitting tolerance, sleep, work capacity and return to normal activity.
Noida Pain Management Clinic, Sector 117
Clinic: WP 01, Sector 117, Noida, UP 201301 | Phone / WhatsApp: +91-7428891444
Chronic Muscle Pain? Get the Right Diagnosis First.
Do not keep treating a trigger point as widespread pain, or widespread pain as a single knot. Book an assessment and get a clear plan for myofascial pain treatment.